The Hidden Neurological Toll of Long COVID: Why This Brain Discovery Changes Everything
This Isn't Just 'Post-Viral Fatigue' – We're Looking at Permanent Brain Rewiring
Let me tell you about something that keeps me awake at night. Not the virus itself, but what it leaves behind in its survivors. For years now, we've heard about long COVID's 'invisible' symptoms – the brain fog, the crushing fatigue, the inexplicable depression. Now, new research reveals something chilling: we're not dealing with temporary inflammation or psychological stress. We're looking at permanent structural damage in the brain's dopamine system. And this changes everything.
The Dopamine Dilemma: Why Motivation Vanishes After COVID
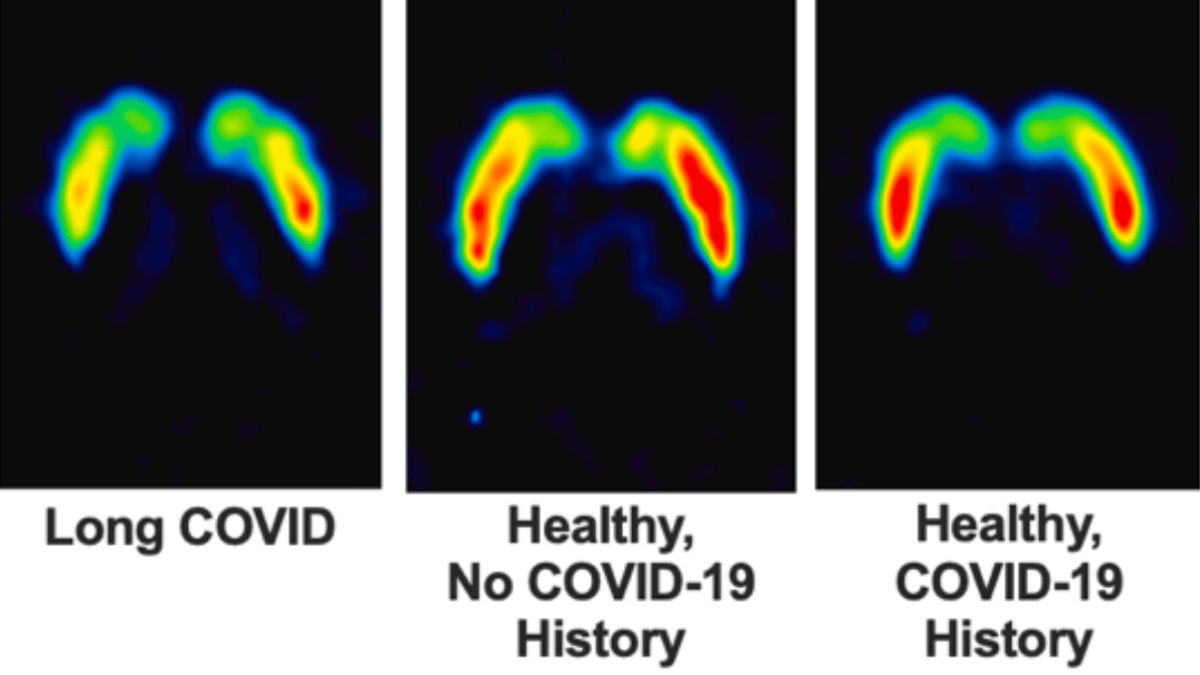
Let's unpack this Canadian study. They found an 18% reduction in dopamine nerve endings in long COVID patients – and this wasn't some vague 'chemical imbalance'. The damage was visible on PET scans, localized in specific brain regions. The ventral striatum damage explains why patients feel like they're moving through molasses mentally. The dorsal striatum loss? That's what makes your body feel like it's betraying you, slowing your movements and speech.
Here's what fascinates me most: dopamine isn't just about feeling good. It's the brain's 'expectation prediction' system. When this gets damaged, your brain can't anticipate rewards or plan effectively. This isn't laziness – it's neurological sabotage. I've spoken to patients who couldn't finish sentences or make grocery lists. Now we understand why.
Why This Research Feels Like a Betrayal of Medical Ethics
Let's get controversial. For three years, medical authorities dismissed long COVID patients as anxious hypochondriacs. Now we have visible brain damage, and suddenly it's 'interesting research'? The cognitive dissonance here is staggering. What this study really proves is that our medical institutions failed catastrophically – not because they couldn't see the damage, but because they refused to look until patients forced their hand.
Consider the implications: if we can detect dopamine system damage, why are we still pushing CBT and graded exercise therapy? Those treatments assume the problem is psychological or deconditioning. With all due respect to the researchers trying to fix this mess now, the damage has been done – to both patients and public trust.
The Dopamine Treatment Gambit: Hope or Hype?
Jeffrey Meyer's upcoming clinical trial using dopamine-modulating drugs feels like a necessary but insufficient step. Let's be honest – we're talking about repurposing medications developed for Parkinson's. While that might help some symptoms, we're missing a crucial point: this isn't just dopamine deficiency. The study shows structural damage to nerve endings. Can we really expect existing drugs to regenerate those connections?
Here's my prediction: this research will split long COVID treatment into two camps. One will focus on damage mitigation – using stimulants or dopamine boosters to manage symptoms. The other will chase nerve regeneration, which might require entirely new therapeutic approaches. The problem? The first approach is cheap and easy; the second could take decades. And patients don't have decades.
Why This Matters Beyond Long COVID
What makes this particularly fascinating is how it reframes our understanding of viral neurology. We've known since polio that viruses can cause physical brain damage. But seeing this level of specificity in dopamine pathways changes the game. Could other viruses – Epstein-Barr, Lyme, even influenza – be causing similar micro-damage we've just never looked for?
This raises a darker question: how many 'mystery illnesses' in medical history were actually undiagnosed dopamine system damage? ME/CFS patients have been dismissed for decades. Now we must wonder – did we lack the technology to see the damage, or the will to look?
The Societal Time Bomb We're Ignoring
Let's talk numbers. Even at the low estimate, 65 million people worldwide have long COVID. If 10-20% of children are affected, we're looking at a generation facing chronic neurological impairment. And what happens when a significant portion of the workforce develops dopamine-related cognitive deficits? We're not just talking healthcare costs – we're talking about fundamental shifts in economic productivity and social structures.
This isn't alarmism – it's realism. The workers of 2030 might literally have less capacity for motivation and complex problem-solving. Companies will need to completely restructure workflows. Education systems must adapt to neurologically altered students. And yet, where's the global task force? The emergency funding? The public urgency?
What This Really Means for You
Here's the truth we must face: long COVID isn't a niche medical issue. It's a societal mirror. The same systems that dismissed early pandemic warnings are now scrambling to catch up with its aftermath. But this research gives us something precious – undeniable proof that we need a complete rethink of post-viral care.
So next time you hear someone minimize long COVID as 'just fatigue', remember those PET scans. Remember the 18% fewer dopamine connections. Because now we know: this wasn't in their heads. It was their heads – and we can see it with our own eyes.